Do the Splits
Build front- or middle-split range gradually with consistent stretching, strength, and patient practice.
 Ask Murph to help
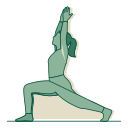
The splits are a specific flexibility skill. A front split mainly needs hamstring range in the front leg and hip-flexor range in the back leg. A middle split leans on hip abduction and adductor tolerance. Pick one version first, because the training differs.
Progress comes from repeated, tolerable exposure over months, plus enough strength to control the new range. Forcing yourself to the floor in one session produces pain more reliably than flexibility.
What to do
- Practice the chosen split three to five days a week after warming up.
- Use static stretches for the main limiting muscle groups.
- Add loaded or active work through the range: split squats, Romanian deadlifts, or controlled lateral lunges.
- Keep hips and stance consistent enough to compare sessions.
- Put supports under the hands or hips instead of hanging passively at the limit.
- Increase depth gradually and don't bounce into end range.
Meta-analysis supports chronic stretching for range of motion, and full-range resistance training can help too. The evidence doesn't set a universal number of minutes or promise everyone the same floor position; anatomy and starting range vary.
A simple plan
For a front split, warm up for five minutes. Do two 30- to 45-second hamstring stretches per side, two hip-flexor stretches, eight slow Romanian deadlifts, and six split squats per side. Then move into a supported front split for three 20-second holds per side.
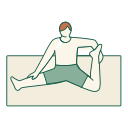
For a middle split, do two adductor stretches, eight controlled lateral lunges per side, and three supported wide-stance holds. Keep feet and knees where they feel stable, with yoga blocks or a chair so the hands can share the weight.
Practice four days a week, two of them slightly easier. Every two weeks, measure the distance from your pelvis to a fixed reference after the same warm-up. Lower the support a little only when the current depth feels controlled.
On a harder day, run the full sequence and use a deeper supported position. On an easier day, shorten the holds and focus on active leg lifts or gentle range. Don't schedule the hardest split work right after exhausting sprint, kicking, or heavy leg training, when coordination and force control drop.
Front-split sides often differ; train both, but give each its own support height rather than forcing the stiffer side to catch up.
How to know it is working
Track support height, distance to the floor, comfort, and whether you can exit the position under your own strength. A photo from the side or front every two to four weeks documents range if the camera stays in the same spot.
Extra range right after a warm-up is expected. Long-term progress means the starting position improves and the deeper range feels less threatening. A full split reached by collapsing onto blocks isn't a controlled one.
If you get stuck
If stretching produces no lasting change, add loaded strength in the relevant range and reduce the intensity of holds. If the front hip pinches, change stance and pelvic position rather than pushing deeper. If the back knee is uncomfortable, add padding or use a standing variation.
Progress often slows near end range. Don't respond by doubling volume; use smaller increases, more recovery, and consistent technique. Bone structure can limit some middle-split positions; a different hip rotation or a comfortable incomplete range may be the right endpoint.